Research program
How do we determine the significance of a genetic variant?
Integrating in vitro and in silico evidence to quantify disease probability rather than relying on binary pathogenicity labels.
Integrating in vitro and in silico evidence to quantify disease probability rather than relying on binary pathogenicity labels.
Sequencing reveals far more variants than anyone can interpret one at a time, and most rare alleles end up “of uncertain significance.” We resolve them by integrating published carriers, functional measurements, protein structure and computational predictors into a probability of disease with explicit uncertainty. Cardiac ion-channel genes for long QT, Brugada and CPVT are our starting point because they connect molecular mechanism to a clinical outcome cleanly. For an overview, watch this talk.
SCN5A variants curated
evidence sources unified
LLM consensus per curation
genes live on VariantBrowser
LLM agents pull carrier counts, phenotypes and study context from PubMed; a multi-model consensus scores gene–disease validity against the ClinGen SOP. Every extraction links back to its sentence in the source.
AlphaMissense, REVEL, CADD, ClinVar and gnomAD are unified into one database so every variant carries the same panel of predictive evidence.
Variants are mapped onto AlphaFold structures with elastic-network analysis, so pathogenic clusters raise the prior for nearby variants of uncertain significance.
A Bayesian model fuses carriers, features and structural priors into a penetrance estimate with full uncertainty. Patented as US-20220406461-A1.
Variant-level estimate. The probability that a heterozygote carrying this variant is affected, averaged over all carriers. This is what VariantBrowser reports, and it is calibrated against published cohorts.
Individual clinical risk. The same variant produces different outcomes in different people because of polygenic background, sex, QTc, age and therapy. Estimating that requires patient-derived models and longitudinal cohorts, which is where the newer projects below sit.
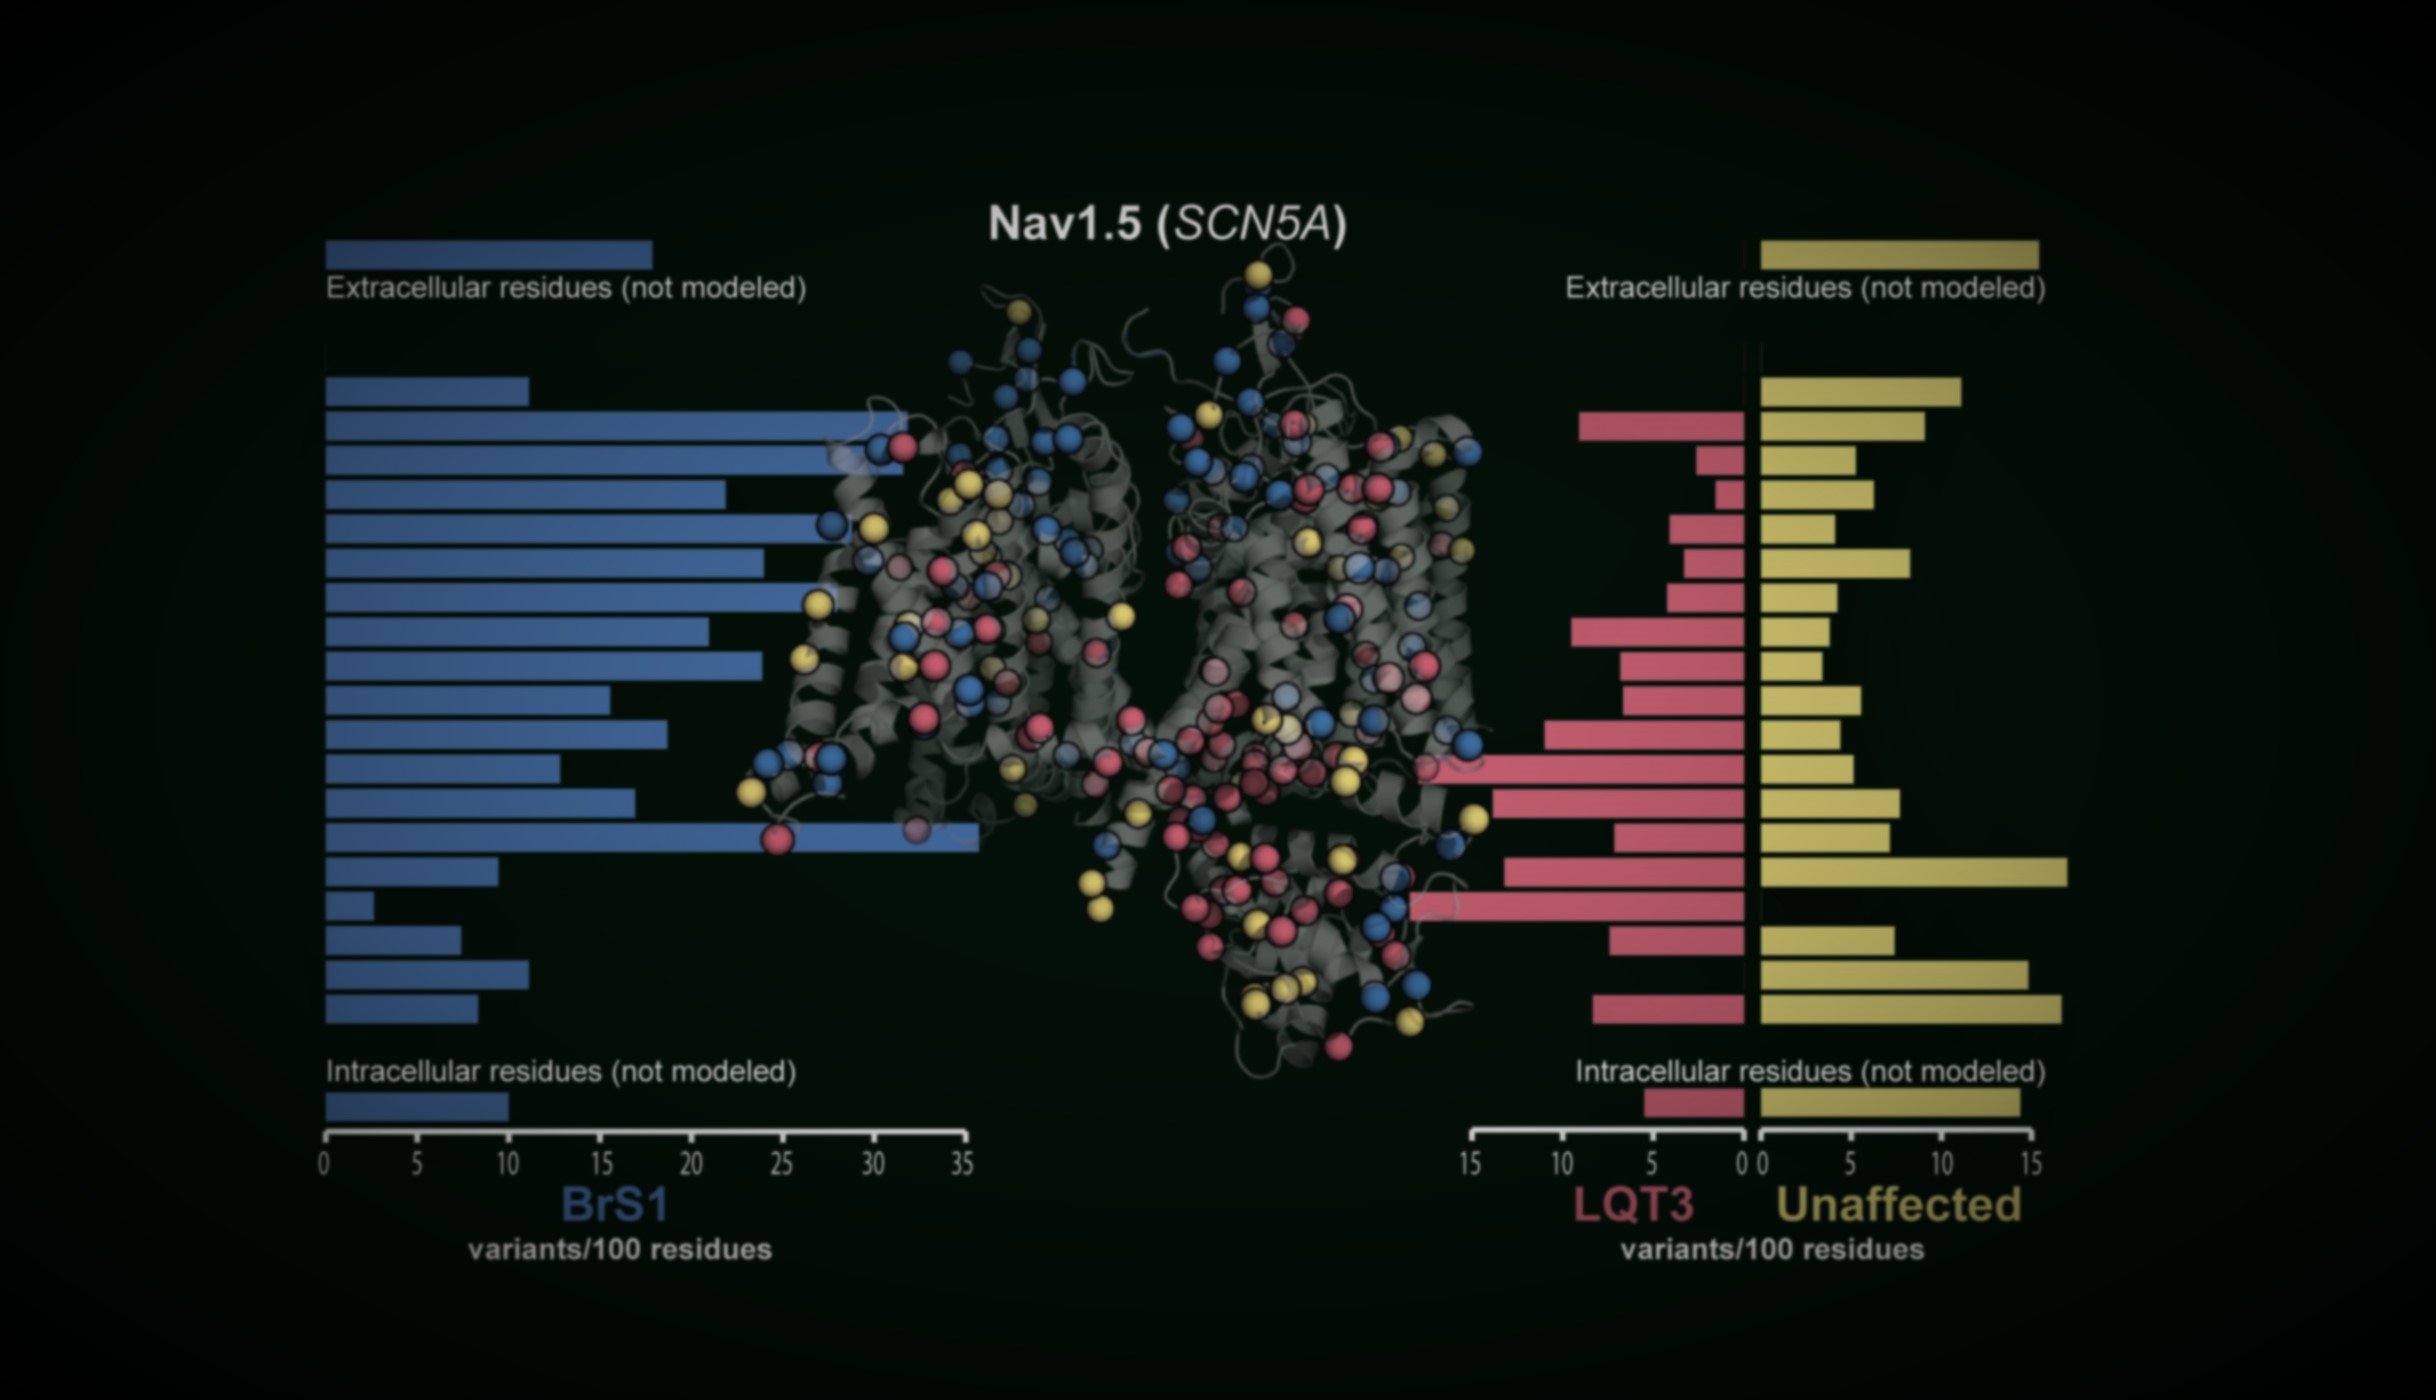
Across more than 1,400 curated SCN5A variants, including 304 with functional data, modest perturbations produce heterogeneous presentations while extreme loss or gain of function produces consistent ones. Carriers of the same variant can still present differently; peak current tracks with, but does not determine, how many are diagnosed with Brugada syndrome.
| Variant | Peak current | Unaffected | BrS1 |
|---|---|---|---|
| S1787N | 95% | 12 | 1 |
| Y1795H | 66% | 7 | 5 |
| R367H | 0% | 3 | 16 |
Peak current is a proxy for channel function; counts are published heterozygotes.
The most complete variant-effect map to date for KCNH2/Kv11.1 trafficking, thousands of variants in one experiment, and a contribution to the CardioVar atlas of variant effects across cardiovascular genes (LDLR, KCNQ1).
With the Vandenberg and Ng labs, a calibrated PS3/BS3 assay for KCNH2 that measurably lowers clinical uncertainty and, combined with MAVE data, improves cardiac-event risk stratification (Circulation 2024).
Patient-derived lines from individuals at the extremes of QT polygenic score, CRISPR-edited rare variants, and an open field-potential analyzer, used to test how genetic background reshapes channel function and drug response.
Quantitative proteomics in iPSC-cardiomyocytes shows how elevated QT polygenic risk reshapes the Kv11.1 (hERG) interaction network around endocytic trafficking, a concrete mechanism linking common variation to repolarization. Rosetta modeling, molecular dynamics and NMR supply the structural priors the penetrance model uses.
With Bastarache and Ruderfer (NHGRI UG3), integrating multimodal data with ML/AI to predict the outcomes that matter most to people who receive a pathogenic result.
We are evaluating survival models in harmonized international KCNH2 cohorts to test whether variant- and patient-specific features can identify carriers at higher risk of cardiac events despite beta-blockers.
The framework is gene-agnostic. Pilots extend LLM-assisted, ClinGen-style curation to atrial fibrillation genes and toward 50 gene–disease pairs with structure-derived features.
Integrating KCNH2 variant-specific features and heterozygote phenotypes to estimate long QT penetrance. PI, 2022–2027.
Systematically mapping variant effects for more than 25 cardiovascular disease genes. Key personnel (Roden, PI), 2022–2026.
Patient-centered prediction of clinically important outcomes arising from pathogenic variants. Co-I (Bastarache/Ruderfer, PIs), 2025–2027.
From QT polygenic extremes to biological mechanisms: a BioVU functional genomics pilot. PI, VUMC, 2026–2027.
Previously: NIH K99/R00 HL135442 (2017–2022), AHA Career Development Award (2021–2024), Leducq Foundation 18CVD05 (2019–2024), NIH R01HL149826 (2020–2023).


